Pages

Tuesday, 31 August 2010

Brisk walks ‘could prevent 10,000 breast and bowel cancers’

source: Times
About 10,000 cases of breast and bowel cancer could be prevented every year in Britain if people quickened their walking pace and became more physically active, researchers say. Scientists believe that up to 4,600 bowel cancer cases and about 5,500 breast cancer cases could be avoided by more brisk walking and other forms of moderate activity, which causes the heart to beat faster and increases breathing.

Physical activity is also known to reduce the risk of endometrial cancer, which affects the womb, as well as helping people trim waistlines. Being overweight or obese is a known risk factor for several types of cancer, as well as heart disease and type 2 diabetes, according to the World Cancer Research Fund (WCRF). 

Rachel Thompson, deputy head of science for the fund, said: “You don’t have to go to the gym every day to benefit. “You can reduce your cancer risk just by making small changes and this is highlighted by the fact that so many cancer cases could be prevented through something as simple as brisk walking. “By taking up walking as a hobby or even walking to the shops instead of taking the bus or car, people can make a real difference to their health.” Dr Thompson said that there was “a lot of work to do” in raising awareness because few people were aware of the link between exercise and cancer risk. Each year, about 13,000 people in Britain die of breast cancer and 16,000 of bowel cancer. 

The WCRF recommends being physically active for at least half an hour a day. However, according to government figures, only 37 per cent of men and 25 per cent of women manage this. 

The latest figures came from a WCRF report that suggested up to 40 per cent of all cancers could be prevented by adjusting lifestyle factors such as losing weight, cutting down consumption of red meat or alcohol and doing more exercise. 

Previously studies have shown that moderate exercise can have a protective effect against breast and bowel cancer and can reduce the risk of lung cancer by as much as 40 per cent.

Friday, 27 August 2010

Traffic Light Adopters & Guideline Daily Amounts (GDA)


reposted from: http://www.food.gov.uk/multimedia/pdfs/tladopters0110.pdf via http://www.eatwell.gov.uk/foodlabels/trafficlights/

From the Marks & Spencer label, the Guideline Daily Amounts (GDA) are:
Cals - 2028 (365*100/18), Sugar - 91g, Fat - 69g, Saturated Fat -  20g, Salt - 6g

From McCain, GDA differ

Cals - 1936 (213*100/11), Sugar - 80g, Fat - 76g, Saturated Fat -  17g, Salt - 5g

This is strange since surely the GDA does not differ eg M&S work out at 6g salt and McCains 5g salt. Whats up?


The European review of labelling reference intake values - Scientific Opinion of the Panel on Dietetic Products (1), (detail pdf) recommended Daily Guideline Amounts:- Energy 2000 kcal, Total fat 70g (31.5 E%) of which Saturated fat 20g (9 E%), Carbohydrate 260g (52 E%) of which Sugars 90g (18 E%), Salt 6g.

(1): Scientific Opinion of the Panel on Dietetic products, Nutrition and Allergies on a request from European Commission on the review of labelling reference intake values for selected nutritional elements. The EFSA Journal (2009) 1008, 1-3

Energy 

The proposed labelling reference intake for energy (8400 kJ or 2000 kcal) corresponds to the recommended energy intake for a moderately active woman. 

Total fat 

The proposed labelling reference intake for total fat (70 g) corresponds to 31.5 E% for a 8400 kJ (2000 kcal) diet. This value is within the range of the upper limits of intake of fat (30 – 35 E%) recommended for individuals in the general population in EU countries and by other authorities. It is at the lower end of the range of average total fat intakes in adults observed in EU countries (about 30 - 47 E%). 

Saturated fat 

The proposed labelling reference intake for saturated fat (20 g) corresponds to 9 E% for a 8400 kJ (2000 kcal) diet. This value is consistent with the upper limits of intake of saturated fat (8 - 10 E%) recommended for individuals in the general population in EU countries and by other authorities. It is at the lower end of the range of average saturated fat intakes in adults in EU countries (about 9 - 18 E%).

Carbohydrate 

The proposed labelling reference intake for carbohydrate (230 g) corresponds to 46 E% for a 8400 kJ (2000 kcal) diet. This is less than the lower limits of intake of carbohydrate (generally 50 - 55 E%) recommended for individuals in the general population in EU countries and by other authorities. 

The Panel proposes that the labelling reference intake for carbohydrate be 260 g (corresponding to 52 E% for a 8400kJ or 2000 kcal diet) which is within the range of lower limits of recommended intakes for individuals in the general population and close to the upper end of the range of average carbohydrate intakes in adults in EU countries.  

Sugars 

The proposed labelling reference intake for (total) sugars (90 g) corresponds to 18 E% for a 8400 kJ (2000 kcal) diet. The proposed value is at the lower end of the range of average intakes of total sugars in adults in EU countries (about 17 - 26 E%). Total sugars include both indigenous (sugars naturally present in foods such as fruit, vegetables, cereals and lactose in milk products) and added sugars. There are generally no recommended intakes for total sugars. Some authorities have recommended upper limits of intake of added sugars (generally 10 E%) for individuals in the general population, while others recommend that intake of added sugars, or certain foods containing added sugars, be limited but do not recommend an upper limit. 

It has been estimated that indigenous sugars provided by recommended daily intakes of fruits, vegetables, cereals and dairy products would amount to about 45 g in adults. Assuming that the remaining 45 g of sugars (up to the 90 g proposed for the labelling reference intake) are added sugars, this would correspond to 9 E% for a 8400 kJ or 2000 kcal diet. 

Thus the Panel considers that the proposed labelling reference intake of 90 g for (total) sugars is compatible with a recommended upper limit of intake of added sugars of 10 E% for individuals in the general population as proposed by some authorities. 

Salt 

The proposed labelling reference intake for salt is 6 g. This value is within the range of the upper limits of intakes of salt (generally 5-8 g) recommended in EU countries and by other authorities. It is less than the lower end of the range of average salt intakes in adults in EU countries (about 8-11 g). 

Published: 4 May 2009 


From a table in the detailed efsa report eg Total Fat 70g x 9 kcal/g = 630 kcal which is 31.5% of a 2000kcal diet. Note: 
  • the 230g (46 E%) carbohydrate was substituted for 260g (52 E%) in the final report.
  • big differences (last column) between men and women eg saturated fat 20g for women / 30g for men


Wednesday, 25 August 2010

Crabsallover Liver Function tests - Serum alanine aminotransferase & Serum total bilirubin

Crabsallover Tested July 2010 (Twin Oaks)
Alanine transaminase (ALT)
  •  Serum alanine aminotransferase: Crabsallover: 25 iu/L (range ex.Twin Oaks : 0-35 iu/L) aka Alanine transaminase (ALT)
    • NOT PRESENT: but if were...elevated levels of ALT suggest viral hepatitis, congestive heart failure, liver damage, bile duct problems, infectious mononucleosis, or myopathy. 
    • NOT PRESENT: but if were.. elevated ALT levels due to liver-cell damage can be distinguished from biliary duct problems by measuring alkaline phosphatase. Myopathy-related ALT levels can be ruled out by measuring creatine kinase. 
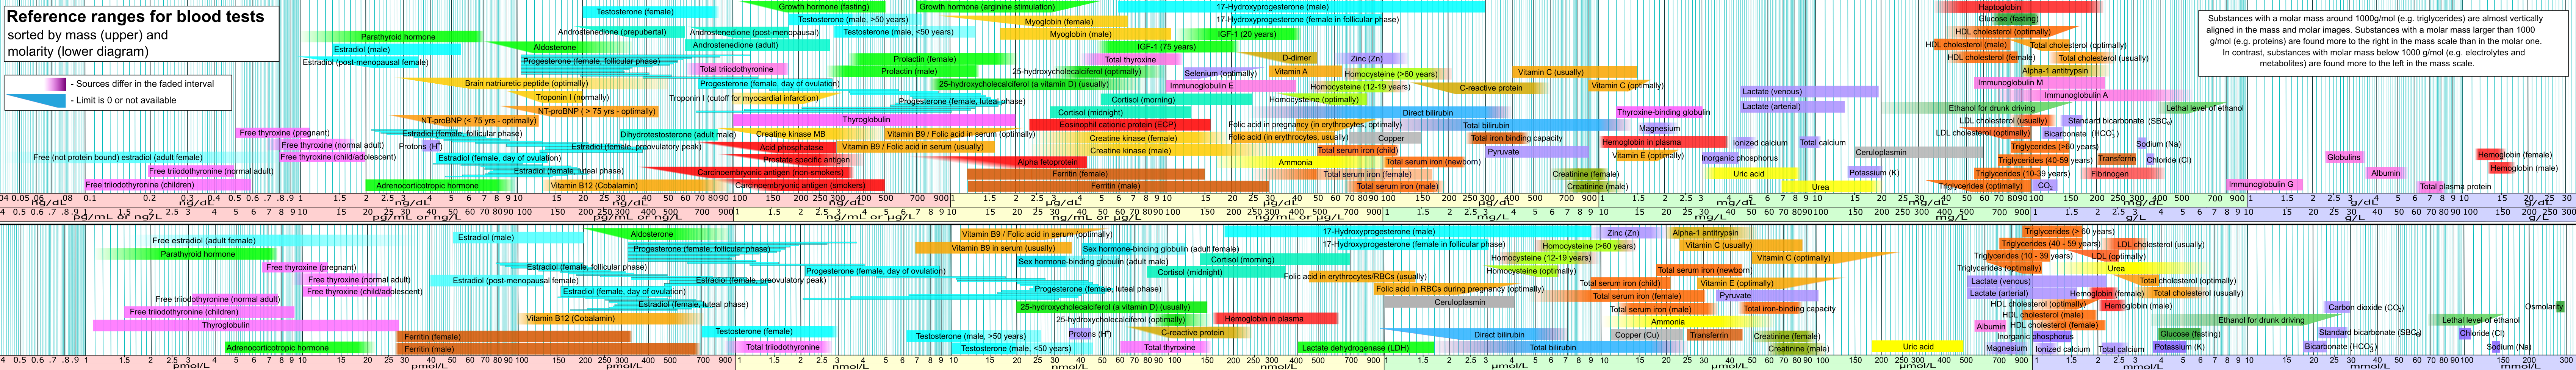
  • Range via Reference ranges for blood 0.15-1 ukat/L
http://en.wikipedia.org/wiki/Reference_ranges_for_blood_tests#By_enzyme_activity
Labtestsonline.org.uk
no levels guidance given

Bilirubin
  • Serum total bilirubin: Crabsallover: 18 umol/L and 20 umol/L on 3/11/11, range (ex. Twin Oaks): 0-17 umol/L 

    •  5.1-17umol/L and some sources 1.5-25umol/L total bilirubin (Reference range for blood tests)
    • Bilirubin is the yellow breakdown product of normal heme catabolism found in hemoglobin. Bilirubin is excreted in urine and is responsible for the yellow color of bruises & urine.
    • High levels of bilirubin in the blood may be caused by:
      • infections eg infected gallbladder, or cholecystitis. 
      • inherited diseases eg Gilbert's syndrome (affects how liver processes bilirubin)
      • Diseases that cause liver damage eg hepatitis, cirrhosis, or mononucleosis. 
      • Diseases that cause blockage of the bile ducts eg gallstones or cancer of pancreas. 
      • Rapid destruction of red blood cells eg sickle cell disease 
    • To elucidate causes of jaundice or increased bilirubin liver function tests (eg alanine transaminase, aspartate transaminase, gamma-glutamyl transpeptidase, alkaline phosphatase), blood film examination (hemolysis, etc.) or evidence of infective hepatitis (e.g., hepatitis A, B, C, delta, E, etc.)
    • high Bilirubin levels can result from red blood cell breakdown or liver disease. Two different chemical forms of bilirubin—direct (or conjugated) and indirect (or unconjugated) bilirubin are tested. If the direct bilirubin is high there may be some kind of blockage of the liver or bile duct, perhaps due to gallstones, hepatitis, trauma, a drug reaction, or long-term alcohol abuse. If the indirect bilirubin is increased, haemolysis (undesirable breakdown of red blood cells) may be the cause.
Conclusion:
Seek further medical opinion - 18 umol/L bilirubin is outside the range (Twin Oaks): 0-17 umol/L

Crabsallover Glucose levels - Diabetes test

November 2011: 4.4 mmol/L (Savage, twin oaks)
July 2010: Glucose 5.2mmol/L (Twin Oaks)
October 2008: Glucose 4.8 mmol/L (Lloyds Pharmacy)
November 2006: Glucose 6.1 mmol/L with a fasting retest: 5.9 mmol/l. (Sharon 4.9 mmol/L, November 2006).

Normal Glucose Range: 4.4 - 6.1 mmol/L (source)

Diabetes is diagnosed by fasting plasma glucose level >7.0 mmol/L. At 5.6 to 6.9 mmol/L levels is 'impaired fasting glucose' (IFG) a pre-diabetic state, associated with insulin resistance and increased risk of cardiovascular pathology. 50% risk over 10 years of IFG progressing to overt diabetes - average time for progression as less than three years.[1] IFG is also a risk factor for mortality.[2]

Conclusion: 
Since November 2006 5.9mmol/L, IFG crabsallover glucose levels have become normal: 4.8 mmol/L (October 2008) and 5.2 mmol/L (July 2010) and  4.4 mmol/L (November 2011)

NB. =5.2 x 18 = 93.6 mg/dL source: http://www.faqs.org/faqs/diabetes/faq/part1/section-9.html